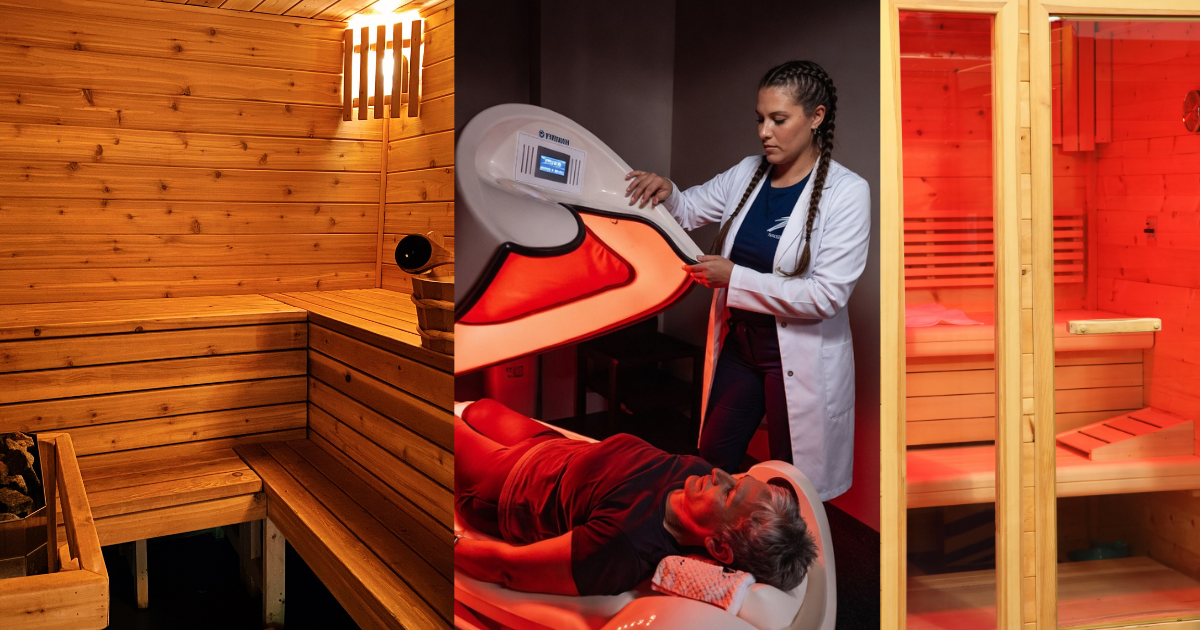
Perimenopause and menopause aren't one thing — they're dozens of things happening at once. The hot flashes that wake you at 3am. The brain fog that makes you feel like a different person. The hair that suddenly fills the shower drain or wraps the ponytail an extra time. The sleep that used to come easily and now won't. The mood that swings in ways that feel foreign. And underneath all of it, a hormonal shift that conventional medicine often addresses with a prescription and a shrug.
There's no single intervention that fixes menopause. But what we see consistently at Lost in Float — and what the research increasingly supports — is that a combination of heat, cold, and nervous system reset may support the physiological systems behind many of the most common symptoms, not just the symptoms themselves.
This is what the protocol looks like, why we think it helps, and what women in Lincoln are actually experiencing.
What's Actually Happening in Your Body
The core hormonal shift of perimenopause and menopause is a decline in estrogen and progesterone — but the downstream effects are widespread. Estrogen is involved in thermoregulation, sleep architecture, mood regulation, cardiovascular function, bone density, skin collagen production, hair follicle activity, and cognitive function. When it drops, all of those systems feel it.
Hot flashes — formally called vasomotor symptoms (VMS) — occur because declining estrogen disrupts the brain's thermostat in the hypothalamus, causing it to misfire and trigger sudden heat dissipation responses. Night sweats are the same mechanism during sleep. Sleep disruption compounds everything else: poor sleep raises cortisol, which worsens mood, impairs cognitive function, drives inflammation, and makes every other symptom harder to manage.
It sounds counterintuitive: deliberately sitting in a 195°F sauna when you're already experiencing unwanted heat events. But the research suggests that intentional, regular heat exposure strengthens the body's thermoregulatory mechanisms. Heat shock proteins — produced during sauna sessions — are linked to estrogen signaling pathways, and their production may decline with declining estrogen, which is one of the working hypotheses for why hot flashes happen at all.
Most menopause-specific RCTs to date have used far-infrared therapy. Chien et al. (2011, Journal of Alternative and Complementary Medicine), for example, found that 20-minute FIR sessions twice weekly for 10 weeks significantly reduced menopause-related symptom scores in postmenopausal women. The underlying thermoregulatory mechanism — heat acclimation training the hypothalamus to respond more efficiently — applies regardless of heat source. For traditional Finnish sauna specifically, the largest cohort study that included women (Laukkanen et al., BMC Medicine, 2018, n=1,688, 51% women) documented significant cardiovascular and longevity benefits, which become especially relevant after menopause when estrogen's protective cardiac effects diminish.
The Full Picture: What Most Women Actually Experience
Perimenopause and menopause involve 30 or more recognized symptoms — and most women experience some combination they didn't expect. Hot flashes and disrupted sleep get the most attention, but they're rarely the only things happening. Hair thinning, in particular, is one of the most underdiscussed and emotionally significant changes — and it's near the top of the list of what brings women to us.
Other shifts that show up routinely include:
- Hair thinning, increased shedding, or loss of volume
- Weight gain around the midsection that doesn't respond to old strategies
- Vaginal dryness, discomfort during intimacy, or pelvic floor changes
- Irregular cycles or heavier bleeding (perimenopause)
- Joint stiffness, fatigue, and brain fog
- Mood shifts, anxiety, and changes in libido
What makes this confusing is how interconnected the symptoms are. Cortisol, circulation, inflammation, sleep architecture, and mitochondrial function affect almost all of them at once. The protocol that follows is designed to support those underlying systems — which may be why many women tell us they notice changes across symptoms they weren't specifically trying to address.
Sauna + Cold Plunge: The Combination Women Ask About Most
The most consistent pattern we hear from women managing menopause centers on one specific combination: traditional sauna followed by cold plunge. Fire & Ice (Sauna + Cold Plunge) — heat to vasodilate, cold to vasoconstrict — creates a vascular "pump" that many women find more noticeable than either one alone.
"I started with float therapy (which I love) then tried Fire & Ice and the benefits have been immeasurable! I can't wait for my next session. The facility is so clean and the staff are so welcoming."
"Absolutely love the Fire and Ice. At first I was skeptical and didn't think I would be able to do the cold plunge, but it was mind over matter and I have gone several times now."
Research on cold plunging for menopause specifically is still limited, but the mechanism is interesting. Cold water immersion triggers norepinephrine release — a study by Šrámek et al. (2000, European Journal of Applied Physiology) documented a 530% increase in plasma norepinephrine and a 250% increase in dopamine after a full hour of immersion in 57°F water, with cortisol decreasing by 34%. A 3–5 minute plunge is a much shorter exposure, so expect a smaller response — but norepinephrine is involved in both mood and thermoregulation, and emerging research suggests regular cold exposure may influence how the autonomic nervous system responds to temperature — the same system involved in hot flashes.
Float Therapy: The Nervous System Reset
The hormonal turbulence of perimenopause keeps the nervous system in a state of chronic activation. Cortisol stays elevated. Sleep stays disrupted. The parasympathetic nervous system — the rest-and-repair mode — struggles to engage. Float therapy's most immediate effect, for many women, is a deep parasympathetic shift — the body's rest-and-repair mode.
"There is no way I could have prepared myself for this. I realized my whole life had turned into a slow crawl. My body has never felt so relaxed and I don't have an urgency to go go go go get everything done. Highly recommend, thanks!"
For women with menopause-driven insomnia, the float tank offers something specific: it may encourage theta brainwave states — the same patterns associated with the transition into deep sleep — without any effort or prescription. Many members describe post-float sleep as the deepest they've had in months. With regular sessions, many members tell us the carry-over effect lengthens — and research suggests floating may support lower cortisol and a calmer nervous system over time.
A meta-analysis of 27 floatation-REST studies (Van Dierendonck & Nijenhuis, Psychology & Health, 2005) documented significant reductions in cortisol and blood pressure alongside improvements in subjective well-being. For women in perimenopause — who often experience elevated cortisol as both a cause and consequence of their symptoms — this cortisol reduction is directly relevant. Lower cortisol may support sleep onset, a calmer mood, and healthy inflammatory balance.
Red Light Therapy: Skin, Collagen, Tissue Support & Scalp
Skin collagen declines by approximately 30% in the first five years of menopause, with continued losses of about 2% per year for the next 15 years — a finding first documented by Brincat et al. (1987) and confirmed across multiple studies since. This is one of the most concrete and measurable biological changes of the transition. Skin becomes thinner, drier, and more prone to fine lines. Wound healing slows. Joint tissues become less resilient.
Research suggests red light therapy may stimulate fibroblast activity and collagen synthesis through photobiomodulation. Our top-of-the-line full-body bed offers 10 wavelengths across the red and near-infrared spectrum (415–980nm), targeted to your goal, and was independently tested by LightLab International at an average of 36.84 mW/cm². This is the range most studied for skin collagen and tissue support.
Connective tissue changes affect more than skin. Declining estrogen also affects joint tissues, ligaments, and the deeper connective structures of the body. The same photobiomodulation mechanisms that support skin collagen — fibroblast activation, improved local circulation, mitochondrial energy production — apply to connective tissue more broadly. For pelvic floor concerns specifically, the most direct research uses targeted intravaginal devices rather than full-body beds, so we'd point women experiencing significant incontinence or genitourinary symptoms toward a menopause-informed provider or pelvic floor specialist as the primary route — and view full-body red light as a complementary tissue-support layer.
The same mechanisms are increasingly studied for scalp health and hair density. We get into that next.
Hair Thinning & Volume Loss in Perimenopause
Hair changes are one of the most distressing parts of perimenopause, and one of the least discussed. The ponytail wraps an extra time. The shower drain fills faster. Volume that used to be a given quietly disappears.
Hair follicles are among the most metabolically demanding tissues in the body. Declining estrogen shortens the active growth phase, while elevated cortisol and shifting androgens push more follicles into the resting and shedding phases. There's typically a 90-day lag between trigger and visible shedding — the hair coming out today is responding to what happened months ago. That same lag works in your favor on the way back: meaningful changes usually take 3–6 months of consistent support to see.
How the protocol supports hair health:
- Red light therapy — the most direct evidence among our services. A double-blind randomized controlled trial by Lanzafame et al. (2014, Lasers in Surgery and Medicine) found that low-level light therapy at 655nm significantly improved hair counts in women with androgenetic alopecia. The FDA cleared photobiomodulation devices for both male and female pattern hair loss in 2007. Female pattern hair loss is the most common form of menopausal thinning.
- Sauna and cold plunge — improved circulation, lowered baseline cortisol, and better stress resilience all reduce shedding triggers.
- Float therapy — direct cortisol reduction. Stress-related shedding (telogen effluvium) is one of the most common contributors during perimenopause.
- Strength training — supports metabolic and hormonal stability that affects follicle behavior over time.
Worth a conversation with your provider: ferritin, full thyroid panel, vitamin D, B12, zinc, and hormones (including free testosterone and SHBG). Hair loss often has multiple contributors, and labs help identify which ones apply to you. Foundational supports like consistent protein intake, morning sunlight, and stable sleep tend to matter more than any single supplement.
Weight, Metabolism & Body Composition
Weight gain around the midsection, slower metabolism, and gradual muscle loss are among the most common perimenopause and menopause changes — and among the most frustrating, because the strategies that worked before often stop working. The shift isn't a willpower problem. Estrogen decline affects insulin sensitivity, where fat is stored, and the body's ability to maintain muscle mass.
What the research and member experience consistently support:
- Strength training 3–4x/week — the single most evidence-backed intervention for preserving muscle, bone density, and metabolic rate through menopause.
- Sauna and cold exposure — both have research support for improved insulin sensitivity and recovery.
- Protein-forward meals and blood sugar stability — supporting muscle maintenance and reducing cortisol-driven cravings.
- Sleep and cortisol management — float therapy's effect here is particularly relevant. Sleep loss and elevated cortisol drive both abdominal fat storage and muscle loss.
The point isn't to chase a specific number on the scale. It's to support the systems — muscle, metabolism, cortisol, sleep — that determine how your body feels and functions through this transition.
The Protocol: What to Actually Do
Based on what the research supports and what we see consistently from members, here is the most effective combination for managing perimenopause and menopause symptoms:
"Of all the menopause symptoms, disrupted sleep cascades most into everything else. Support sleep, and everything else gets easier."
The Sleep Problem — and Why It's the Priority
Of all the menopause symptoms, disrupted sleep cascades most into everything else. Poor sleep raises cortisol. Elevated cortisol impairs the brain's ability to consolidate memory, regulate mood, and manage temperature. It worsens hot flash frequency. It drives the anxiety and low-grade depression that many perimenopausal women experience.
The sleep combination members ask about most in the Lost in Float toolkit is sauna and float on the same evening. The sauna raises core body temperature; the post-sauna temperature drop signals sleep onset to the brain with unusual clarity. The float, later in the evening, may support theta brainwave states and cortisol reduction that many members describe as producing sleep deeper than anything since their twenties.
For women with menopause-driven insomnia, we'd suggest starting here: one float session per week, ideally in the early evening. Track your sleep that night. The feedback is usually immediate enough to be its own motivation.
"Lost in Float has provided me a source of healing and regeneration beyond my expectations. I absolutely love to float. It's very clean, safe and inviting here. The staff are wonderful, warm and kind."
"If you are considering a service at Lost in Float I urge you to just DO IT, now. You will wish you had done it sooner. They offer unique services that are so incredibly good for your body and soul."
Build your protocol in Lincoln
Sauna, cold plunge, float, red light, and strength training — all under one roof. Open Tuesday–Sunday, 9am–9pm. When you're ready, we'd love to see you.
Book a session → See membershipsThis protocol complements medical care — it doesn't replace it. Talk to a menopause-informed provider about heavy or unexpected bleeding (especially any bleeding after 12 consecutive months without a period), severe fatigue, joint pain with swelling, sudden or rapid hair loss, or symptoms that aren't improving with foundational support. Conditions like thyroid imbalance, anemia, and nutrient deficiencies can mimic or worsen menopausal symptoms and are worth ruling out. A menopause-informed provider can walk you through the full range of medical options. Jot down your symptoms and what you’ve tried for a few weeks and bring that with you — concrete pattern data makes the conversation more useful.
Frequently Asked Questions
A note: This post is based on published research and member experience. It is not medical advice. Perimenopause and menopause management is individual — what works varies significantly by person, symptom profile, and health history. Continue working with your healthcare provider, and bring this protocol into that conversation.